EGFR-Mutant Non-Small Cell Lung Carcinoma: Molecular Pathology, Tyrosine Kinase Resistance & Osimertinib
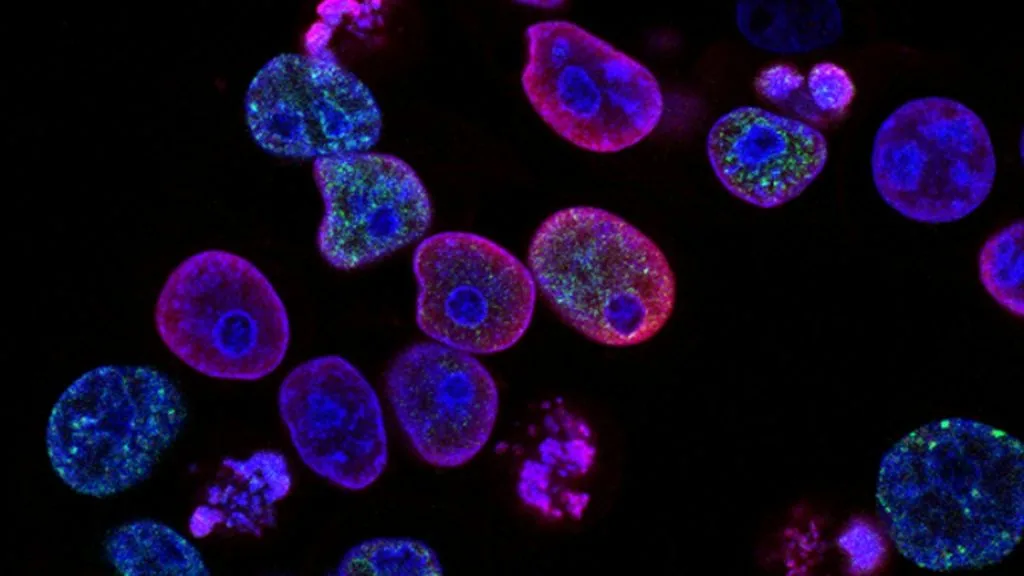
EGFR-mutant non-small cell lung carcinoma is an aggressive pulmonary malignancy defined by oncogenic mutations in the epidermal growth factor receptor gene. It represents approximately fifteen percent of all non-small cell lung cancer diagnoses in Western populations.
- Primary molecular driver: In-frame exon 19 deletions or L858R point mutation in ERBB1.
- First-line standard of care: Third-generation irreversible EGFR-TKI (Osimertinib 80mg PO QD).
- Primary mechanism of resistance: T790M gatekeeper mutation or C797S tertiary resistance.
The disease predominantly manifests in lifelong non-smokers and female patients diagnosed with pulmonary adenocarcinoma. High-resolution thoracic computed tomography imaging regularly reveals peripheral pulmonary nodules accompanied by regional lymphadenopathy.
Activating mutations in the **EGFR** kinase domain constitutively stimulate downstream pro-survival signaling cascades. This sustained enzymatic activation drives unregulated cellular proliferation and inhibits intrinsic apoptotic pathways.
CLINICAL & LABORATORY DIAGNOSTIC PROTOCOL
- Specimen acquisition: Core needle biopsy or resection fixed in 10% neutral-buffered formalin (NBF) within 30 minutes of devascularization (cold ischemia time < 1 hr).
- Tissue processing: Formalin fixation time strictly calibrated to 24–48 hours at room temperature; paraffin embedding with 4-micron microtome sectioning on positively charged slides.
- Control standards: On-slide external positive control tissue and validated negative isotype control run in parallel with every analytical batch.
Tissue Deparaffinization & Heat-Induced Epitope Retrieval (HIER)
Bake slides at 60°C for 60 minutes, deparaffinize through sequential xylene baths (3 x 5 min), and rehydrate through graded ethanols (100%, 95%, 70%) to deionized water. Perform HIER in target retrieval solution (pH 9.0 EDTA buffer or pH 6.0 citrate buffer) at 97°C for 20 minutes in a calibrated PT Link module.
Endogenous Peroxidase Block & Primary Antibody Incubation
Quench endogenous peroxidase activity using 3% hydrogen peroxide for 10 minutes. Apply optimized primary monoclonal antibody (e.g., clone 22C3, SP263, or 4B5) at calibrated clinical dilution and incubate for 30–60 minutes at room temperature in a humidified chamber.
Polymer Detection System & DAB Chromogen Visualization
Rinse in Tris-buffered saline with 0.05% Tween-20 (TBST). Apply horseradish peroxidase (HRP)-conjugated anti-rabbit/mouse polymer secondary reagent for 30 minutes. Incubate with freshly prepared 3,3-diaminobenzidine (DAB) substrate-chromogen solution for 5-10 minutes until brown precipitates develop.
Counterstaining, Dehydration & Quality Control Scoring
Counterstain nuclei with Mayer hematoxylin for 1–2 minutes, blue in running tap water or 0.08% ammonia water, dehydrate through graded ethanols, clear in xylene, and coverslip with permanent non-aqueous mounting medium. Score tumor cell membrane/nuclear staining under light microscopy using validated scoring algorithm.
1. Pathophysiology, Etiology & Cellular Carcinogenesis
Pulmonary carcinogenesis initiates through somatic mutagenesis of alveolar type II pneumocytes or bronchiolar stem cells. Environmental exposures and stochastic DNA replication errors induce structural alterations within critical proto-oncogenes.
Epigenetic dysregulation characterized by aberrant promoter hypermethylation silences tumor suppressor genes including **CDKN2A** and **TP53**. This chromatin condensation bypasses critical cell cycle checkpoints, facilitating unregulated genomic instability.
The surrounding tumor microenvironment exhibits dense desmoplastic stroma and immunosuppressive regulatory T-cell infiltration. Hypoxia-inducible factor 1-alpha upregulation drives vascular endothelial growth factor secretion and pathological neoangiogenesis.
2. Oncogenic Signal Transduction Pathways & Genomic Alterations
Ligand-independent receptor dimerization triggers constitutive autophosphorylation of intracellular tyrosine residues within the **ERBB1** receptor. These phosphorylated docking sites recruit downstream adaptor proteins that permanently lock the receptor in an active conformation.
Aberrant signal propagation immediately bifurcates into the **RAS-RAF-MEK-ERK** and **PI3K-AKT-mTOR** intracellular kinase cascades. These parallel networks upregulate protein synthesis, inhibit pro-apoptotic proteins, and accelerate cellular proliferation.
Acquired resistance frequently emerges through secondary gatekeeper mutations or activation of bypass tracks such as **MET** amplification. These biochemical bypass loops restore downstream signal transduction despite sustained pharmacological receptor blockade.
3. Histopathological Grading, Morphological Subtypes & Differential Diagnosis
Histopathological examination reveals distinct architectural growth patterns including acinar, papillary, micropapillary, and solid subtypes. Neoplastic cells display pronounced nuclear atypia, prominent nucleoli, and abundant amphophilic cytoplasm.
Immunohistochemical profiling utilizes a precise panel featuring **TTF-1** positivity and **Napsin A** co-expression. Squamous differentiation markers such as **p40** and **CK5/6** must remain negative to confirm pulmonary adenocarcinoma.
Diagnostic differentials require the exclusion of metastatic adenocarcinomas originating from the gastrointestinal tract, breast, or thyroid. Comprehensive clinical correlation and site-specific transcription factor panels resolve ambiguous histological presentations.
4. Targeted Therapeutics, Landmark Phase III Trials & Resistance Mechanics
First-generation reversible tyrosine kinase inhibitors like gefitinib competitively bind the ATP pocket of **EGFR**. Third-generation agents such as **osimertinib** form covalent bonds with the **C797** residue, achieving superior central nervous system penetration.
The landmark **FLAURA** Phase III trial demonstrated a statistically significant overall survival benefit favoring **osimertinib** over older generation inhibitors. Median progression-free survival reached 18.9 months in the frontline metastatic cohort.
Acquired tertiary resistance frequently involves the **C797S** point mutation preventing covalent drug binding. Novel fourth-generation inhibitors and bispecific antibody combinations are currently under investigation to overcome these specific conformational roadblocks.
5. Molecular Staging, Minimal Residual Disease (ctDNA) & Prognostic Stratification
Staging relies on the AJCC 8th edition TNM classification integrating tumor dimension, lymph node involvement, and distant metastasis. Molecular profiling using next-generation sequencing is mandatory for establishing baseline actionable genomic landscapes.
Liquid biopsy surveillance utilizing circulating tumor **DNA (ctDNA)** permits highly sensitive minimal residual disease detection. Serial plasma assays identify emerging resistance mutations months before radiographic disease progression.
Prognostic stratification relies on comprehensive genomic burden scoring alongside traditional clinicopathological parameters. Integration of these modalities optimizes therapeutic sequencing and refines long-term survival expectations.